
 Printed on: November 12th, 2026
Disclaimer
Please note, once printed or downloaded, articles cannot be updated. By bookmarking the article and continuing to access it online, you can be sure you are reading the most up-to-date information and that you are not in breach of copyright laws.
This Pearl is provided as free content. Here is the link to our terms of use
Screening for and preventing type 2 diabetes
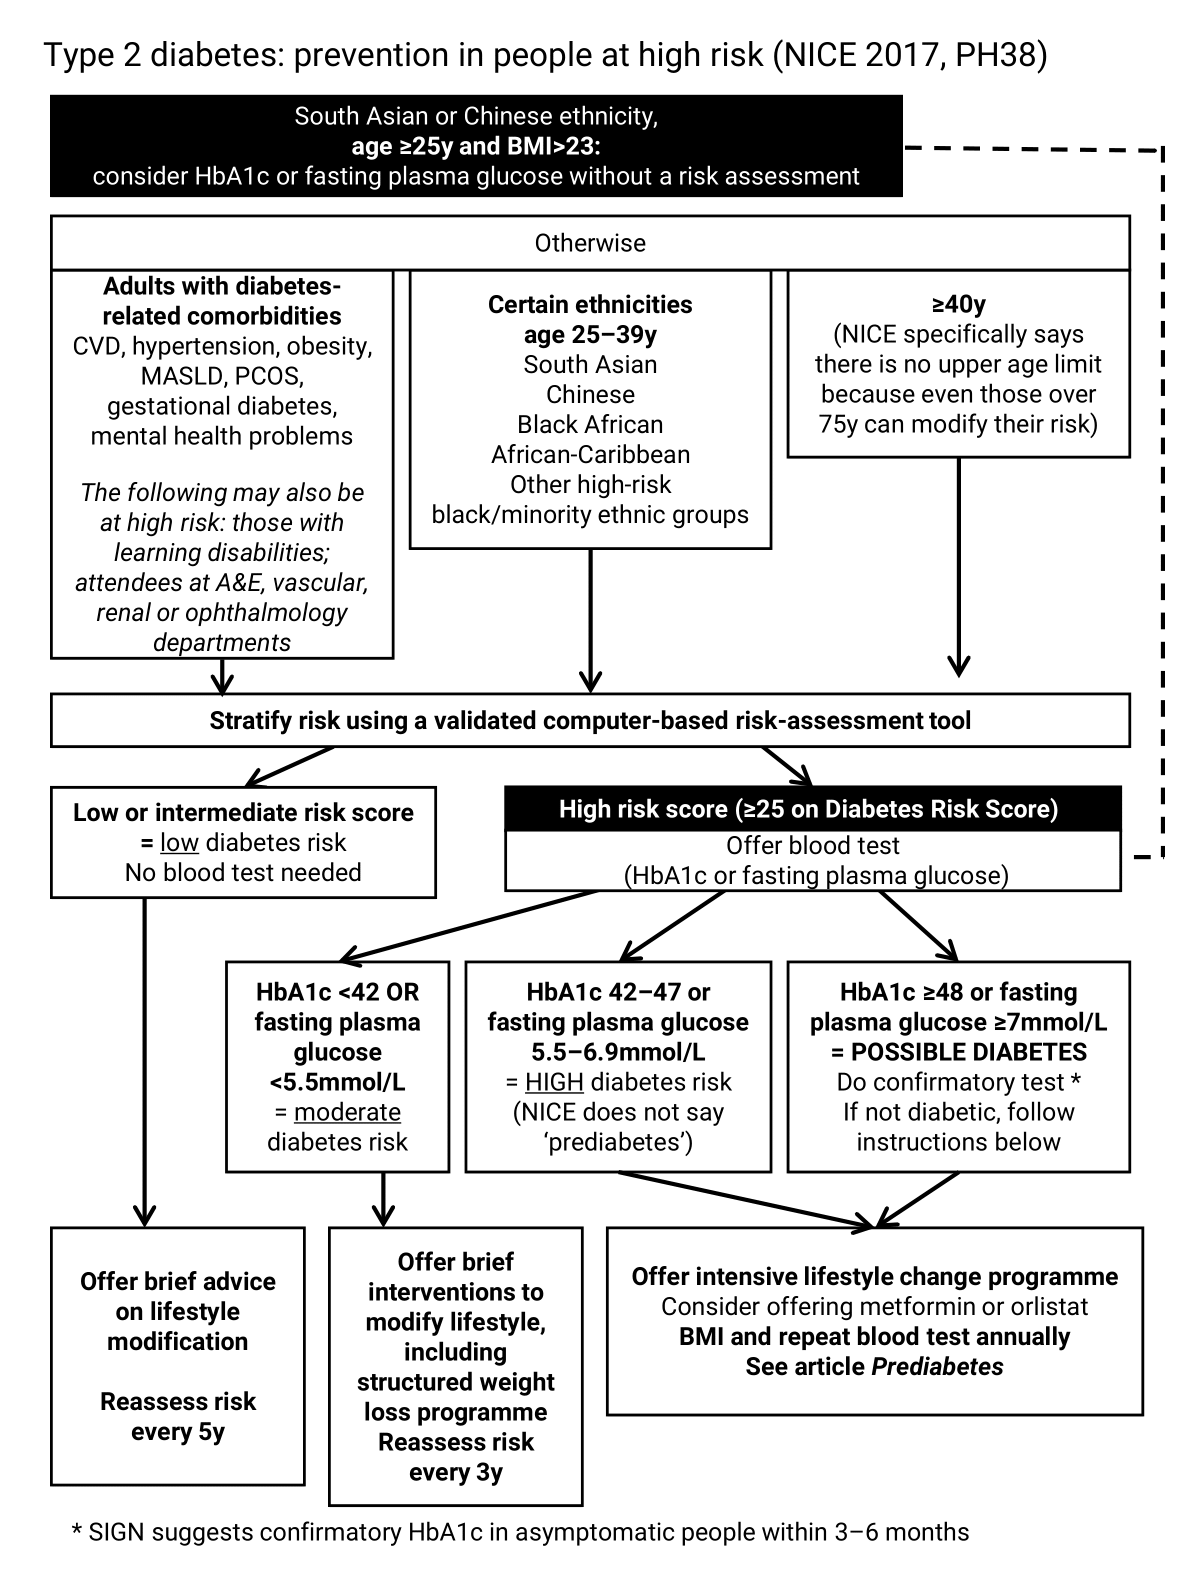
NICE published its public health guidance on screening for diabetes and prediabetes in 2017; it was broadly unchanged from the previous 2012 iteration (NICE 2017, PH38). In 2025, SIGN stepped in with fresh guidance which broadly agrees with NICE PH38, and has additional information on remission, ultra-low-calorie diets, GLP-1 mimetics and tirzepatide for prediabetes (SIGN 2025, 172). Here, we summarise the (rather complicated!) guidance. But, first – is screening for diabetes worth it?
This article was last updated in June 2026.
Is screening for and treating prediabetes worth it?
Yes! (JAMA 2023;329:1206)
- Clinical trials show that progression to diabetes can be prevented with intensive lifestyle modification.
- Interventions improve macrovascular and possibly microvascular outcomes.
All this is discussed in more detail in the article Prediabetes.
‘Know your diabetes risk’
Diabetes UK encourages people to use an online score to assess their diabetes risk. Those who use the risk score and are at increased risk (a moderate or high score) are encouraged to seek a screening blood test from their GP.
The Know Your Risk score asks about:
- Sex.
- Age.
- Ethnicity.
- Height and weight.
- Waist circumference.
- Personal history of hypertension.
- Family history of diabetes in a first-degree relative.
Could you add a link on your practice website or display in the waiting room?
NICE guidance on screening for diabetes and prediabetes
In 2019, the UK National Screening Committee declared that population-level screening was not supported by evidence.
Instead, NICE asks us to perform targeted screening.
The guidance asks us to screen a LOT of people, but the screening work isn’t just for us – community pharmacists, dentists, opticians, community leaders, occupational health teams and those working in prisons, as well as people providing services for those with learning disabilities, are all encouraged to identify high-risk patients and risk stratify them (and then send them to us for the blood test!), or get patients to do this for themselves via the Diabetes UK website (see useful resources, below, for the link).
The key message is that, for most, the guidance recommends a two-stage screening process:
- Stage 1: assess risk of diabetes in high-risk people. This should be done using a validated scoring tool, similar to QRISK for CVD risk.
- Stage 2: in those deemed high risk on the scoring tool, do a blood test (HbA1c or fasting plasma glucose) and offer the appropriate intervention according to the result of the blood test.
Which risk scoring tool should I use?
NICE does not recommend a particular risk scoring tool; it gives examples of the Leicester and Cambridge scores (which can interrogate clinical record systems) or the Diabetes Risk Score (which the patient completes with data such as height, weight, waist circumference and family history). SIGN suggests QDIABETES or the Diabetes UK Know Your Risk score. Below, we summarise the NICE guidance, which broadly aligns with SIGN.
The ‘eyeball’ test and BMI in minority ethnic groups
Are we objective when offering screening? Or do we subjectively administer the ‘eyeball’ test (i.e. ‘guess the BMI’) then decide if they warrant screening? It turns out that the ‘eyeball’ test is not particularly accurate!
Most GPs tend to underestimate people’s BMI. We know this from a study that showed GPs photos of people and asked them to classify them as underweight, healthy weight or overweight (BJGP 2014;64:e703). Of course, remote consulting is making this even worse because we don’t even get the visual cue that weight may be an issue!
Another problem with remote consulting is that we may forget about the differential risk of BMI in different ethnicities.
A massive study from the UK CPRD compared the diabetes risk for different ethnicities (Lancet Diabetes Endocrinol 2021;9:419-26). Taking the risk of developing diabetes in a White person with a BMI of 30, the equivalent risk occurred at much lower BMIs in other ethnicities:
| Ethnic groups (self-classified) | Compared with a White person with a BMI of 30, the equivalent risk of developing diabetes over the next 6.5 years occurred at these BMIs |
| South Asian | 23.9 |
| Arab | 26.6 |
| Chinese | 26.9 |
| Black | 28.1 |
| BMI cut-offs for overweight and obesity in the UK (SIGN 2025, 172) | ||
| Ethnicity | BMI lower cut-off for ‘overweight’ | BMI lower cut-off for obesity |
| White | 25.0 | 30.0 |
| South Asian | 19.2 | 23.3 |
| Black or African-Caribbean | 23.4 | 25.9 |
| Arab | 22.1 | 26.6 |
| Chinese | 22.2 | 24.6 |
What does this mean in practice?
- ‘Eyeballing’ is not a good enough way to work out whether people are overweight (and it REALLY doesn’t work when remote consulting!).
- Ethnicity affects risk, and some ethnicities have a much higher risk of diabetes at normal, or just above normal, BMIs.
- This is one of the reasons that the NICE guidance says:
- Those of certain ethnicities should be offered a diabetes risk assessment from 25y, even in the absence of obvious risk factors.
- Consider a screening HbA1c in those of South Asian or Chinese ethnicity without doing a risk assessment first if age ≥25y and BMI >23.
 |
Screening for and preventing type 2 diabetes
|
 |
What do you and your practice currently offer to those at high risk of diabetes? How might this change in light of the NICE guidance and the drive to detect more diabetes? |
 |
Useful resources: Websites (all resources are hyperlinked for ease of use in Red Whale Knowledge)
|
This information is for use by clinicians for individual educational purposes, and should be used only within the context of the scope of your personal practice. It should not be shared or used for commercial purposes. If you wish to use our content for group or commercial purposes, you must contact us at sales@red-whale.co.uk to discuss licensing, otherwise you may be infringing our intellectual property rights.
Although we make reasonable efforts to update and check the information in our content is accurate at the date of publication or presentation, we make no representations, warranties or guarantees, whether express or implied, that the information in our products is accurate, complete or up to date.
This content is, of necessity, of a brief and general nature, and this should not replace your own good clinical judgment or be regarded as a substitute for taking professional advice in appropriate circumstances. In particular, check drug doses, side effects and interactions with the British National Formulary. Save insofar as any such liability cannot be excluded at law, we do not accept any liability for loss of any type caused by reliance on the information in these pages.
Here is the link to our terms of use.